Does GLP-1 Affect Blood Sugar Even If You Are Using It for Weight Loss?
Yes. GLP-1 medicines can affect blood glucose levels whether they are prescribed for type 2 diabetes or weight management. They act on systems involved in appetite, digestion and blood-sugar regulation, so their effects are not limited to the reason a person starts treatment.
For someone without diabetes, that does not automatically mean their blood sugar will become too low or that they will develop a problem. The likelihood of a blood-sugar issue depends on the medicine, other medicines a person takes, their health and how treatment is monitored. Understanding what GLP-1 medicines do—and what they do not do—can help people make a safer, more informed decision.
What GLP-1 medicines do in the body
GLP-1 stands for glucagon-like peptide-1, a hormone released by the gut after eating that helps coordinate appetite, digestion and blood-sugar control. Medicines called GLP-1 receptor agonists mimic some of this hormone’s effects by activating GLP-1 receptors.
You know what's funny? these medicines can help the body release insulin when blood glucose is high, reduce the release of glucagon (a hormone that can raise blood sugar), and slow how quickly food leaves the stomach. They can also influence appetite and fullness signals in the brain. The mix of these actions is why GLP-1 medicines may have both blood-sugar effects and weight-management effects.
Weight loss is not simply a matter of willpower. Appetite and body weight are influenced by biology, health conditions, medicines, sleep, stress, food access and many other factors. For some people, GLP-1 treatment changes hunger and fullness enough to make a lower-energy eating pattern more achievable; it is not a test of character or effort.
What happens to blood glucose levels during weight-loss treatment?
GLP-1 medicines can lower blood glucose, but they generally encourage insulin release in response to higher glucose rather than forcing insulin release continuously. This glucose-dependent action helps explain why the risk of hypoglycaemia—blood glucose that is lower than the body needs—is usually low when a GLP-1 medicine is used on its own by someone without diabetes.
That risk can be different when the medicine is combined with other treatments. Insulin and sulfonylureas (medicines that prompt the pancreas to release insulin) can cause low blood sugar. Someone taking either may need a clinician to review their doses when starting a GLP-1 medicine, particularly if their food intake falls substantially.
Even without diabetes, eating much less than usual, vomiting, diarrhoea or dehydration can leave a person feeling unwell. Symptoms such as sweating, shakiness, dizziness, confusion or unusual weakness can have several causes, including low blood glucose. A clinician can advise whether testing is appropriate and what action to take; symptoms should not be automatically attributed to the medicine.
Does a lower reading mean the medicine is working?
Not necessarily. A change in blood glucose is not the only measure of whether weight-management treatment is suitable or effective. Clinicians consider the person’s health, weight-related conditions, side effects, treatment goals and the medicine’s licensed use. Routine blood-glucose monitoring may not be needed for every person without diabetes, but monitoring decisions should be made individually.
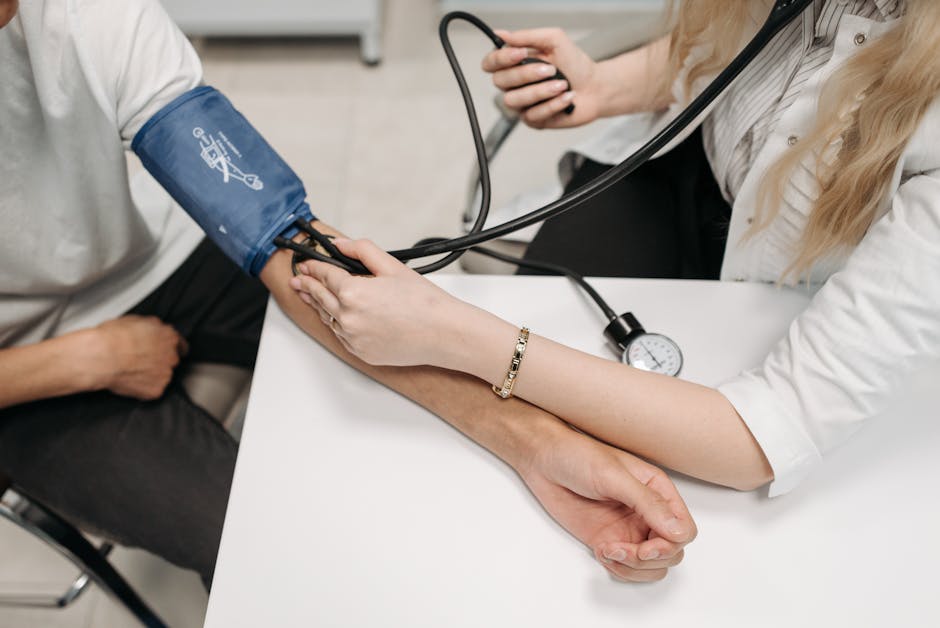
For a person with diabetes, clinicians may use measures such as fasting glucose or HbA1c. HbA1c is a blood test that estimates average blood glucose over roughly the previous two to three months. The right checks and timing depend on the person’s treatment plan and existing conditions.
Satiety, food noise and the mental load of eating
Satiety is the feeling of fullness and satisfaction after eating that helps signal when to stop a meal. By affecting gut-to-brain signalling and slowing stomach emptying, GLP-1 medicines can make fullness last longer for some people and reduce appetite.
Some people also describe a reduction in “food noise”: persistent, distracting thoughts about food, cravings or the next opportunity to eat. This is a common expression, not a formal medical diagnosis, and people’s experiences vary. For some, less preoccupation with food reduces the mental load of planning and resisting cravings. Others notice little change, or find that side effects make eating more difficult.
These experiences are connected to appetite regulation, but they are not a substitute for overall care. A medicine does not address every reason someone may eat in a particular way, and reduced appetite does not guarantee adequate nutrition. A prescriber may discuss practical meal planning, hydration and support that fits the person’s circumstances.
Metabolic benefits—and important limits
Metabolic benefits are changes in the way the body handles processes such as blood sugar and, in some cases, weight-related health risks. In people with type 2 diabetes, some GLP-1 medicines are used to improve blood-glucose management. In people prescribed them for weight management, weight loss may also improve some markers of metabolic health, although results differ from person to person.
A medicine’s effect on glucose does not mean it is appropriate for everyone, or that it prevents diabetes in every person who uses it. Nor should a person stop, start or adjust diabetes treatment based on weight-loss results without clinical advice. The indication, dose, expected benefits and safety checks depend on the specific product and the individual.
Oral GLP-1 access: convenience is not the same as suitability
Oral GLP-1 treatment means taking a GLP-1 medicine by mouth rather than by injection. A tablet may be more convenient for some people, but oral and injectable products can have different instructions, evidence, doses and licensed uses. A tablet formulation should not be assumed to be interchangeable regulated pharmacy assessment with an injection.
In the UK, availability and authorised indications can change. Check the current product information and MHRA status for the exact medicine, including whether it is authorised for type 2 diabetes, weight management or another use. Some oral GLP-1 products have been authorised for diabetes rather than weight loss; a medicine’s presence on the market does not mean it is approved for every purpose. Do not rely on online claims or a product name alone to establish its intended use.
Tablets may also have specific timing or administration instructions, such as taking them with limited water before food or other medicines. These rules vary by product and matter for absorption. A pharmacist or prescriber should explain the instructions for the particular medicine before treatment begins.
How the MHRA approval pathway and pharmacy assessment fit in
The MHRA approval pathway is the UK process through which the Medicines and Healthcare products Regulatory Agency assesses medicines for quality, safety and effectiveness before authorising them for specified uses. The authorised product information sets out the medicine’s licensed indication, dosing and safety details; approval does not mean it is suitable for every person.
A private pharmacy clinical assessment is a consultation in which a qualified prescriber or pharmacist reviews whether treatment is appropriate for an individual. It should involve relevant medical history, current medicines, eligibility and safety risks—not simply an online purchase form. In Scotland, people should also consider how private prescribing fits with any care they receive through the NHS and share relevant information with their usual clinician.
Before starting a GLP-1 medicine, a proper assessment should clarify:
- Which product is being considered and whether its current UK authorisation covers the intended use.
- Whether the person meets the relevant eligibility criteria and has any conditions that affect safety.
- Whether other medicines, especially insulin or sulfonylureas, need review.
- How side effects will be managed, what follow-up is planned and whom to contact with concerns.
- How the medicine will be obtained from a legitimate, regulated source.
Prescribing and supply are separate from promotion: a pharmacy’s commercial interest should not replace an independent clinical decision. Be wary of services that promise a particular result, minimise risks or offer treatment without an adequate assessment.

Side effects and when to seek advice
Nausea, vomiting, diarrhoea, constipation and abdominal discomfort are common side effects of GLP-1 medicines, particularly during dose increases. Eating smaller portions, following product-specific advice and keeping up fluids may help, but persistent or severe symptoms need clinical attention. A prescriber should explain the titration schedule—the planned gradual increase in dose—and when to pause or seek advice.
Get urgent medical help for severe, persistent abdominal pain, especially if it spreads to the back or occurs with vomiting. Seek prompt advice if you cannot keep fluids down, feel faint or become markedly unwell. Do not change a prescribed dose or stop another medicine without discussing it with a clinician, unless you have been given specific instructions for an emergency.
Questions to ask before starting
- Is this exact medicine authorised in the UK for weight management, and do I meet its eligibility criteria?
- How could it affect my blood glucose levels alongside my current medicines?
- What monitoring is appropriate for me, and when will we review progress and side effects?
- If I am considering an oral option, what are its specific administration instructions and licensed use?
- What support is available if appetite changes make it hard to eat or drink enough?
The bottom line
GLP-1 medicines can affect blood glucose even when prescribed for weight loss because their gut hormone effects influence both appetite and glucose regulation. Last month, I was working with a client who thought they could save money but ended up paying more.. In people without diabetes who take them alone, clinically significant low blood sugar is generally less likely, but other medicines, reduced food intake and illness can change the picture. Eligibility, product authorisation, monitoring and follow-up matter as much as convenience.
Weight management is not a moral test, and medication is not a universal solution. A safe next step is a qualified clinical assessment that considers the person’s health and preferences, checks the current MHRA-authorised use of the product and sets out a clear plan for review.